Acute kidney injury (AKI) is a serious and as yet incompletely understood disorder in which sudden impairment of kidney function occurs secondary to one or more of a variety of underlying conditions. This disorder is very common in (elderly) ICU patients and is associated with very high mortality. Many of those who survive suffer from permanent kidney failure and other long-term morbidities, which may include cardiovascular disease and immune dysfunction. Epidemiologic evidence suggests that AKI is not a single disease, but a syndrome comprised of multiple, often coexisting, etiologies. Being usually part of multiorgan failure syndrome, it calls for multiple organ support therapy. The publication at hand contains sections on prerenal azotemia syndromes, dying 'of' or 'with' AKI, pathophysiology of sepsis-induced acute kidney injury, developments in prevention / treatment / rehabilitation, and renal support. Reporting the latest recommendations from experts, it provides valuable information for those that are interested in understanding the disorder and its treatment options.

- 266 pages
- English
- ePUB (mobile friendly)
- Available on iOS & Android
eBook - ePub
Controversies in Acute Kidney Injury
About this book
Information
Topic
MedicineSubtopic
Internal Medicine & DiagnosisPrerenal Azotemia Syndromes
Kellum JA, Ronco C, Vincent J- L (eds): Controversies in Acute Kidney Injury.
Contrib Nephrol. Basel, Karger, 2011, vol 174, pp 33-45
Contrib Nephrol. Basel, Karger, 2011, vol 174, pp 33-45
______________________
Cardiorenal Syndrome: A Complex Series of Combined Heart/Kidney Disorders
Ching Yan Goha,c · Grazia Vizzib,c · Massimo De Calb,c · Claudio Roncob,c
aDepartment of Nephrology, Selayang Hospital, Selangor, Malaysia; bDepartment of Nephrology, Dialysis & Transplantation, Ospedale San Bortolo, San Bortolo, and cInternational Renal Research Institute Vicenza (IRRIV), Vicenza, Italy
______________________
Abstract
Over the last decade, it has become increasingly clear that the cardiovascular and renal systems are interdependent. Primary disorders of either system have been shown to disturb the other system. As a result, a class of cardiorenal syndrome (CRS) has been identified wherein a vicious cycle is established in which acute/chronic dysfunction of either the kidney or the heart exacerbates the loss of function in the other organ. The ADQI organization has proposed a classification derived from a consensus conference held in 2008. CRS is classified as a disorder of the heart and kidneys whereby acute or chronic dysfunction in one organ may induce acute or chronic dysfunction in the other. The general definition has been expanded into five subtypes: CRS type 1 = acute worsening of heart function (acute heart failure-acute coronary syndrome) leading to kidney injury and/or dysfunction; CRS type 2 = chronic abnormalities in heart function (chronic heart failure-chronic heart disease) leading to kidney injury or dysfunction; CRS type 3 = acute worsening of kidney function (acute kidney injury) leading to heart injury and/or dysfunction; CRS type 4 = chronic kidney disease (chronic kidney disease) leading to heart injury, disease and/or dysfunction; and CRS type 5 = systemic conditions leading to simultaneous injury and/or dysfunction of heart and kidney. A major problem with previous terminology was that it did not allow for identification of pathophysiological interactions occurring in the different types of combined heart/kidney disorders. The subdivision into different subtypes seems to provide a better approach to this syndrome.
Copyright © 2011 S. Karger AG, Basel
Cardiorenal syndromes (CRS) are broadly defined as conditions characterized by the initiation and/or progression of renal insufficiency secondary to heart failure [1], and it has also been used to describe the negative cardiac effects of declining renal function (renocardiac syndrome) [2]. A recent definition and classification system has been generated to include a vast array of acute or chronic conditions in these two important organs, where the primary failing organ can be either the heart or the kidneys [3]. Such classification has been endorsed and further developed by the ADQI (Acute Dialysis Quality Initiative) consensus group leading to a comprehensive characterization of the complex heart-kidney organ crosstalk [4]. This new classification represents a step forward to a better understanding of the pathophysiology and management strategies of the bidirectional heart-kidney interactions.
The Definition or Classification of Cardiorenal Syndromes
Any direct and indirect insult to either heart or kidneys can initiate and perpetuate the combined disorder of these two organs through several complex mechanisms. Therefore, ‘cardiorenal syndromes’, a large umbrella term, should be used to describe a series of heart and kidney disorders whereby acute or chronic dysfunction in one organ may induce acute or chronic dysfunction (structural or functional abnormalities) of the other. A more descriptive classification into five different subtypes would permit recognition of the primary organ dysfunction (cardiac vs. renal) as well as the acute versus chronic nature of the condition [4]. The five subtypes of the CRS can be identified (table 1) and defined as follows:
• Acute cardiorenal syndrome (CRS type 1): an acute worsening of heart function (acute heart failure-acute coronary syndrome) leading to kidney injury and/or dysfunction.
• Chronic cardiorenal syndrome (CRS type 2): chronic abnormalities in heart function (chronic heart failure-coronary heart disease) leading to kidney injury and/or dysfunction.
• Acute renocardiac syndrome (CRS type 3): acute worsening of kidney function (acute kidney injury) leading to heart injury and/or dysfunction.
• Chronic renocardiac syndrome (CRS type 4): chronic kidney disease leading to heart injury, disease and/or dysfunction.
• Secondary cardiorenal syndromes (CRS type 5): systemic conditions causing simultaneous injury and/or dysfunction of both the heart and kidneys.
The relevant mechanisms are summarized in figure 1.
Pathophysiology of Cardiorenal Syndromes
Type 1 CRS - Acute Cardiorenal Syndrome
Premorbid renal dysfunction is common in heart failure patients [de novo acute heart failure (AHF) or acute decompensated heart failure (ADHF)] and predisposes them to acute kidney injury (AKI), which has been associated with higher risk of prolonged/re-hospitalization, cardiovascular (CV) and all-cause mortality, and faster progression to chronic kidney disease (CKD) stages 4-5 [5-9]. The incidence estimates for AKI or worsening renal function (WRF) associated with AHF and acute coronary syndrome range between 24-45 and 9-19%, respectively [4]. The broad range in reported incidence is largely attributable to variations in the definitions of WRF as well as retrospective and/or post-hoc analysis data collection [5-9].
Table 1. Modern definition of CRS
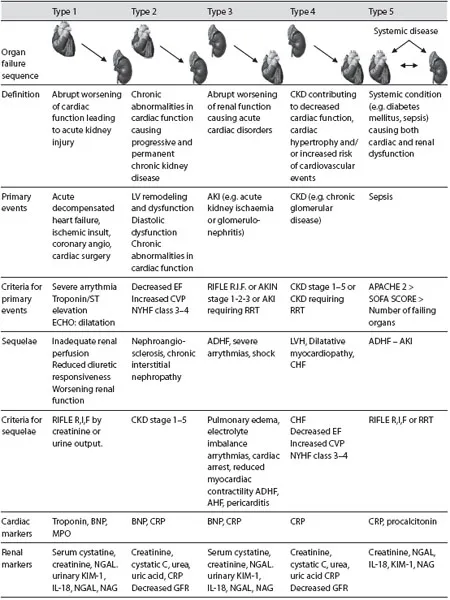
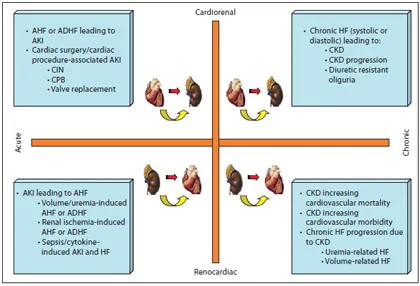
Fig. 1. CRS domain map. The timeframe and the bidirectionality of the different syndromes are described in the different subtypes (acute and chronic; cardiorenal and renocardiac). Every syndrome is then susceptible of transforming into another due to instauration of vicious circles. HF = Heart failure; CIN = contrast-induced nephropathy; CPB = cardiopulmonary bypass.
The mechanisms by which the onset of AHF or ADHF leads to AKI are multiple and complex [6]. They have been widely described in recent publications [3, 4]. The clinical importance of each of these mechanisms is likely to vary from patient to patient. The identified involved mechanisms are hemodynamic mechanisms in which a reduced cardiac output, together with an increased renal venous congestion may affect intrarenal circulation and glomerular filtration rate. Neurohormonal biofeedback mechanisms including reninangio-tensin-aldosterone system activation, a nonosmotic secretion of vasopressin and a parallel sympathetic nervous system-mediated vasoconstriction may lead to perpetuation and extension of the primary insult. We may also suggest an immune-mediated damage where the activation of monocytes and the direct effect of proinflammatory mediators may play an important role in renal tissue apoptosis and damage [10]. Finally, exogenous nephrotoxic agents such as contrast media, aminoglycosides, diuretics or angiotensin-converting enzyme inhibitors may represent another important source of kidney insult in patients with AHF or ADHF.
Humoral Signaling in CRS Type 1
The multiple factors involved in the development of AKI during heart failure describe a pathogenesis of AKI accounting for multiple pathways. Nevertheless, the occurrence of AKI even in patients with preserved or intact ejection fraction, the worsening of renal function even in the absence of fall in cardiac output, and the concept that AKI does not necessarily mean acute tubular necrosis have recently spurred new interest in humoral signaling and the inflammatory pathways to explain distant organ damage and, in particular, kidney injury in heart failure. It is known that ADHF implies an increase in circulating cytokines, but the level of this inflammatory response has not been quantified and it has not been determined in single patients.
We performed a study on 16 patients with ADHF analyzing renal function throughout hospital admission. Eight of the patients developed AKI according to the RIFLE criteria. In all patients we collected serum samples to analyze the possibility of different inflammatory patterns in patients with or without AKI development. Urea creatinine and brain natriuretic peptides (BNP) were not significantly different at admission in the two groups (A = AKI; B = non-AKI) and the amount of diuretics administered was similar. Serum samples collected at admission in all patients were incubated with human monocytic cultured cells (U-937) and the level of apoptosis was evaluated up to 96 h. Our hypothesis was that patients who develop AKI might have an inflammatory pattern due to various mediators that induce an early pathological apoptosis in normal monocytes. In this case, the humoral signal for a distant organ effect could be proved demonstrating an important contribution of the inflammatory pathway to the development of CRS type 1. In figure 2, cell apoptosis is reported in the two groups, demonstrating a significant difference at various incubation time points.
This is the first piece of evidence that CRS type 1 is an inflammatory disorder or at least the contribution of the inflammatory pathways in its pathogenesis is fundamental for the occurrence of distant organ damage.
Type 2 CRS - Chronic Cardiorenal Syndrome
Chronic heart failure patients with secondary WRF are associated with significantly increased adverse CV mortality and prolonged hospitalization. However, chronic heart disease and CKD frequently coexist in the same patient, and often the clinical scenario does not permit the ability to distinguish which disease came first. Notably, there are about 45-63.6% of chronic heart failure patients who have evidence of CKD with an estimated glomerular filtration rate <60 ml/min/1.73 m2 [11, 12]. The mechanisms causing secondary WRF in these patients likely differ from CRS type 1. Concomitant hemodynamic alterations with poor cardiac contractility and neurohormonal abnormalities with excessive production of vasoconstrictive mediators (epinephrine, angiotensin, endothelin), as well as altered sensitivity and/or release of endogenous vasodilatory factors (natriuretic peptides, nitric ...
Table of contents
- Cover Page
- Front Material
- Unveiling Current Controversies in Acute Kidney Injury
- Analysis of the Prerenal Contributions to Acute Kidney Injury
- The Role of Tubuloglomerular Feedback in the Pathogenesis of Acute Kidney Injury
- Can We Identify Prerenal Physiology and Does It Matter?
- Cardiorenal Syndrome: A Complex Series of Combined Heart/Kidney Disorders
- Hepatorenal Syndrome
- Clinical Consequences of Acute Kidney Injury
- Renal-Pulmonary Crosstalk
- Acute Kidney Injury, Acute Lung Injury and Septic Shock: How Does Mortality Compare?
- Sepsis and Acute Kidney Injury Are Bidirectional
- Pathophysiology of Sepsis-Induced Acute Kidney Injury: The Role of Global Renal Blood Flow and Renal Vascular Resistance
- Septic Acute Kidney Injury: The Glomerular Arterioles
- Kidney Endothelial Dysfunction: Ischemia, Localized Infections and Sepsis
- The Pathogenesis of Acute Kidney Injury and the Toxic Triangle of Oxygen, Reactive Oxygen Species and Nitric Oxide
- Pathogenesis of Acute Kidney Injury: Effects of Remote Tissue Damage on the Kidney
- A Role for Oxidative Stress
- Pathophysiology of Acute Kidney Injury to Chronic Kidney Disease: Maladaptive Repair
- Models of Preventable Disease: Contrast-Induced Nephropathy and Cardiac Surgery-Associated Acute Kidney Injury
- Acute Kidney Injury in Children: Prevention, Treatment and Rehabilitation
- Delayed Kidney Allograft Function - What Does It Tell Us about Acute Kidney Injury?
- Acute Kidney Injury Leading to Chronic Kidney Disease and Long-Term Outcomes of Acute Kidney Injury: The Best Opportunity to Mitigate Acute Kidney Injury?
- Role of Microvesicles in Acute Kidney Injury
- Controversies in Acute Kidney Injury: Effects of Fluid Overload on Outcome
- Does Renal Replacement Therapy Improve Outcome? Controversies in Acute Kidney Injury
- Why Did Dose Trials Fail?
- Renal Replacement Therapy: When to Start
- Renal Replacement Therapy for Acute Renal Injury: We Need Better Therapy
- Author Index
- Subject Index
Trusted by 375,005 students
Access to over 1.5 million titles for a fair monthly price.
Study more efficiently using our study tools.
Frequently asked questions
Yes, you can cancel anytime from the Subscription tab in your account settings on the Perlego website. Your subscription will stay active until the end of your current billing period. Learn how to cancel your subscription
No, books cannot be downloaded as external files, such as PDFs, for use outside of Perlego. However, you can download books within the Perlego app for offline reading on mobile or tablet. Learn how to download books offline
Perlego offers two plans: Essential and Complete
- Essential is ideal for learners and professionals who enjoy exploring a wide range of subjects. Access the Essential Library with 800,000+ trusted titles and best-sellers across business, personal growth, and the humanities. Includes unlimited reading time and Standard Read Aloud voice.
- Complete: Perfect for advanced learners and researchers needing full, unrestricted access. Unlock 1.5M+ books across hundreds of subjects, including academic and specialized titles. The Complete Plan also includes advanced features like Premium Read Aloud and Research Assistant.
We are an online textbook subscription service, where you can get access to an entire online library for less than the price of a single book per month. With over 1.5 million books across 990+ topics, we’ve got you covered! Learn about our mission
Look out for the read-aloud symbol on your next book to see if you can listen to it. The read-aloud tool reads text aloud for you, highlighting the text as it is being read. You can pause it, speed it up and slow it down. Learn more about Read Aloud
Yes! You can use the Perlego app on both iOS and Android devices to read anytime, anywhere — even offline. Perfect for commutes or when you’re on the go.
Please note we cannot support devices running on iOS 13 and Android 7 or earlier. Learn more about using the app
Please note we cannot support devices running on iOS 13 and Android 7 or earlier. Learn more about using the app
Yes, you can access Controversies in Acute Kidney Injury by J. A. Kellum,C. Ronco,J. -L. Vincent, Claudio Ronco in PDF and/or ePUB format, as well as other popular books in Medicine & Internal Medicine & Diagnosis. We have over 1.5 million books available in our catalogue for you to explore.