Experts in otorhinolaryngology as well as medical genetics have contributed their reviews to this comprehensive compilation. Introductory chapters deal with basic genetics followed by chapters devoted to specific disorders. The gamut of otorhinolaryngological diseases from both adult and pediatric practice is covered. Included are common disorders such as hearing loss, cleft lip and palate, and thyroid cancers as well as further chapters on rare disorders such as Usher syndrome, neurofibromatosis type 2 and paraganglioma. Also, emerging fields of genetic investigation including otitis media, chronic rhinosinusitis and gene therapy are discussed. The contributions focus on diagnosis and management, as well as practical issues like how to order genetic testing or refer to a medical geneticist or genetic counselor. This publication will serve as an educational and reference text for both adult and pediatric otorhinolaryngologists, as well as medical geneticists and genetic counselors. It will provide readers with an understanding of the current state of genetic disorders seen in ORL practice, allow for accurate diagnosis, and improve patient management.

eBook - ePub
Medical Genetics in the Clinical Practice of ORL
- 166 pages
- English
- ePUB (mobile friendly)
- Available on iOS & Android
eBook - ePub
Medical Genetics in the Clinical Practice of ORL
About this book
Information
Topic
MedicineSubtopic
Communication StudiesAlford RL, Sutton VR (eds): Medical Genetics in the Clinical Practice of ORL.
Adv Otorhinolaryngol. Basel, Karger, 2011, vol 70, pp 84-90
Adv Otorhinolaryngol. Basel, Karger, 2011, vol 70, pp 84-90
______________________
Multiple Endocrine Neoplasia: Types 1 and 2
Deborah J.Marsha · Oliver Gimmb,c
aHormones and Cancer Group, Kolling Institute of Medical Research, Royal North Shore Hospital, University of Sydney E25, St. Leonards, N.S.W., Australia; bDepartment of Surgery and cInstitute for Clinical and Experimental Medicine (IKE), University Hospital, Linköping, Sweden
______________________
Abstract
Multiple endocrine neoplasia type 1 (MEN 1) and type 2 (MEN 2) are autosomal-dominantly inherited syndromes where highly penetrant germline mutations predispose patients to the development of tumours in hormone-secreting cells. In the case of MEN 1, loss-of-function germline mutations in the tumour suppressor gene MEN1 increase the risk of developing pituitary, parathyroid and pancreatic islet tumours, and less commonly thymic carcinoids, lipomas and benign adrenocortical tumours. In the case of MEN 2, gain-of-function germline mutations clustered in specific codons of the RET proto-oncogene increase the risk of developing medullary thyroid carcinoma (MTC), phaeochromocytoma and parathyroid tumours. Offering RET testing is best practice for the clinical management of patients at-risk of MEN 2, and MEN 2 has become a classic model for the integration of molecular medicine into patient care. Prophylactic thyroidectomy in an asymptomatic RET mutation carrier to address the risk of developing MTC can prevent or cure this malignancy. No similar preventative strategies can be employed to prevent or cure MEN 1-associated tumours. Genetic testing for MEN 1 is therefore both more complex due to a general lack of mutational hotspots, and the benefit to patients is less straight forward. While a number of genotype-phenotype correlations exist in MEN 2, providing further rationale for performing genetic testing in this condition, these correlations are absent in MEN 1. This review summarises our current knowledge of these two syndromes with emphasis on those aspects with specific relevance to the otorhinolaryngologist.
Copyright © 2011 S. Karger AG, Basel
Multiple endocrine neoplasia (MEN) types 1 and 2 are part of a group of rare familial endocrine neoplasia disorders characterised by the presence of tumours in hormone secreting cells along with other disorders including von Hippel-Lindau disease, familial paraganglioma and phaeochromocytoma, Cowden syndrome, hyperparathyroidism jaw-tumour syndrome and Carney complex (reviewed in Marsh and Zori [1]). MEN 1 and MEN 2 fall at either end of the spectrum when considering both the ease of conducting genetic testing, and the ability to act on genetic information to prevent or cure a tumour.
Multiple Endocrine Neoplasia Type 1
Clinical Presentation/Phenotype
MEN 1 has been estimated to occur in between 1 in 10,000 to 1 in 100,000 people [2] and is characterised by neuroendocrine tumours of the gastro-enteric-pancreatic tract. These lesions include parathyroid tumours causing primary hyperparathyroidism (pHPT), pancreatic islet cell tumours, anterior pituitary tumours, and less commonly thymic carcinoids, lipomas, thyroid tumours, benign tumours of the adrenal cortex, and atypically generally benign tumours of the adrenal medulla (phaeochromocytoma); however, presentation can vary markedly between two individuals (table 1)
Table 1. Clinical presentations of patients with MEN 1 and MEN 2
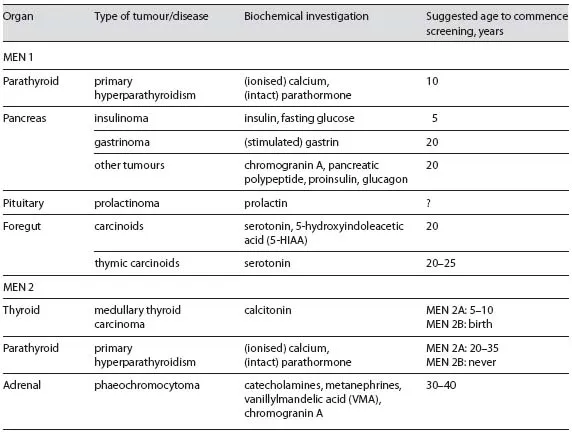
Diagnostic criteria for MEN 1 specifies that an individual must have abnormalities in at least two of the more commonly affected endocrine glands, as well as a first-degree relative with at least one MEN 1-related lesion or a known MEN1 mutation [3]. Almost 50% of MEN 1 patients will succumb to MEN 1-related disease, most frequently associated with pancreatic islet cell tumours [4]. Almost all patients with MEN 1 develop pHPT that can lead to hypercalcemia throughout their lifetime, and although this is almost always benign, its recurring nature can make surgical management difficult. In comparison to sporadic pHPT, these patients typically present between 20 and 25 years of age, approximately 30 years earlier than their sporadic counterparts [5]. Biochemical screening is recommended from the age of 10 years. The underlying genetic cause implies that all parathyroid glands can be affected. In fact, by the time of diagnosis, most patients already present with multiple parathyroid gland enlargement classified as either parathyroid hyperplasia or multiple adenomas. In MEN 1 patients, the diagnosis of pHPT is made if both parathyroid hormone (PTH) and ionised calcium levels are elevated [6].
Genetic Background/Genotype
Germline mutations in the tumour suppressor gene MEN1 were first identified in 1997 in patients with MEN 1 [7, 8]. MEN1 mutations are also found rarely in the related condition Familial Isolated Hyperparathyroidism (FIH). MEN1 consists of 10 exons, where exon 1 is not translated. It encodes the 610 amino acid (67 kDa) ubiquitously expressed and predominantly nuclear protein menin that has roles in the regulation of transcription, controlling genome stability, the regulation of cell division and cell cycle control. Up to 90% of MEN 1 patients will have a MEN1 mutation, with approximately 10% of these mutations appearing to be de novo, i.e. identified in patients with apparently sporadic parathyroid adenomas [9].
Mutations are predicted to be loss of function and include small (and less frequently large) deletions, small insertions, insertion-deletions, as well as nonsense and missense point mutations and splicing mutations, with the majority predicted to prematurely truncate menin [10, 11]. There are over 570 mutation entries for MEN1 in The Human Genome Mutation Database, Cardiff, UK (http://www.hgmd.cf.ac.uk/ac/index.php), and well over 1,000 mutations reported in total [11], with mutations covering the entirety of the gene. There is some indication of potential mutational hot-spots at codons 83-84, 516 and 210-211 accounting for approximately 12% of all mutations [11]; however, in general, lack of frequent mutational clusters complicates genetic screening for this disorder. Of note, in MEN 1 patients without MEN1 mutation, germline mutations in one of the cyclin-dependent kinase inhibitor genes have been reported; however, these would appear to be rare [12].
Genotype-Phenotype Correlations
No appreciable genotype-phenotype correlations have been identified in MEN 1 [11, 13, 14].
Genetic Screening
Knowledge of a patient's MEN1 mutation carrier status is useful for clinical management strategies and life-planning decisions, but cannot avoid or cure the malignancies associated with this condition [3]. This is largely because there are no options for prophylactic surgery for MEN 1 patients, who are generally not treated until their condition first manifests. Biochemical screening to search for early disease in asymptomatic mutation carriers is recommended. If a member of a family tests negative for a MEN1 mutation that is present in affected family members, this removes them from the lifelong burden of biochemical and radiological screening for associated tumours. Guidelines have been published outlining recommended diagnostic tests and therapy for MEN1 mutation carriers [5, 10].
Surgery and Experimental Therapies
The indication to operate is given in any MEN 1 patient with the diagnosis of pHPT. Prior to primary surgery, sophisticated imaging techniques are generally not recommended since their sensitivity is low in MEN 1-associated pHPT [15]. Due to the fact that MEN 1-associated pHPT is a multiglandular disease, an attempt must be made to identify all parathyroid glands intraoperatively. This implies routine removal of the thyrothymic ligament where parathyroid glands can be found in up to 20% of patients. Once all parathyroid glands are localised, the smallest gland should be identified. A remnant about half the size of a normal gland should either be left in situ (referred to as subtotal parathyroidectomy) or be autotransplanted (referred to as total parathyroidectomy and autotransplantation). The other parathyroid glands shall be removed completely. As recurrence of the preserved tissue is common, if subtotal parathyroidectomy is performed the remnant should be marked with a non-absorbable suture or clip in order to facilitate reoperation [15].
Calcimimetics, calcium-sensing receptor agonists, show promise for the treatment of sporadic pHPT and may have a role in treating elevated PTH in the context of MEN 1 [5, 16, 17]. Depot long-acting octreotide has also been used to treat MEN 1-associated pHPT [18]. Multicentre, randomised clinical trials still need to be conducted in order to assess the efficacy of these experimental therapies.
Multiple Endocrine Neoplasia Type 2
Clinical Presentation/Phenotype
MEN 2 is believed to occur in 1 in 200,000 live births [19]. The clinical presentation of MEN 2 may vary significantly between two individuals and includes pHPT, medullary thyroid carcinoma (MTC; a malignant tumour of parafollicular thyroid C cells that secrete calcitonin) and phaeochromocytoma (phaeo; tumour of the adrenal medulla) (table 1). If two or more of these tumours are present in 1 patient or in a close relative, a diagnosis of MEN 2 should be considered. Around two thirds of people harbouring a RET mutation will develop one or more of these tumours by 70 years of age [20].
Clinically and genetically, two major types can be distinguished, namely MEN 2A and MEN 2B. In contrast to MEN 2A, patients with MEN 2B present with a Marfanoid habitus, mucosal neuromas (which often cause the lips to appear large and patulous) and ganglioneuromatosis of the gastrointestinal tract that are clues for thi...
Table of contents
- Cover Page
- Front Matter
- Genetic Basis of Conditions Commonly Seen in ORL Practice
- Basic Medical Genetics for the Otolaryngologist
- Ordering Genetic Tests and Interpreting the Results
- Referring Patients for a Medical Genetics Consultation and Genetic Counseling
- Towards an Etiologic Diagnosis: Assessing the Patient with Hearing Loss
- Nonsyndromic Hereditary Hearing Loss
- Hereditary Hearing Loss with Thyroid Abnormalities
- Pigmentary Anomalies and Hearing Loss
- Usher Syndrome: Hearing Loss with Vision Loss
- Genetic Disorders with both Hearing Loss and Cardiovascular Abnormalities
- Hearing Loss Disorders Associated with Renal Disease
- Multiple Endocrine Neoplasia: Types 1 and 2
- Neurofibromatosis Type 2
- Hereditary Paragangliomas
- Genetic Causes of Nonsyndromic Cleft Lip with or without Cleft Palate
- Chronic Rhinosinusitis
- Otosclerosis
- Genetics of Vestibulopathies
- Genetics of Otitis Media
- Gene Therapy for Head and Neck Cancer
- Author Index
- Subject Index
Trusted by 375,005 students
Access to over 1.5 million titles for a fair monthly price.
Study more efficiently using our study tools.
Frequently asked questions
Yes, you can cancel anytime from the Subscription tab in your account settings on the Perlego website. Your subscription will stay active until the end of your current billing period. Learn how to cancel your subscription
No, books cannot be downloaded as external files, such as PDFs, for use outside of Perlego. However, you can download books within the Perlego app for offline reading on mobile or tablet. Learn how to download books offline
Perlego offers two plans: Essential and Complete
- Essential is ideal for learners and professionals who enjoy exploring a wide range of subjects. Access the Essential Library with 800,000+ trusted titles and best-sellers across business, personal growth, and the humanities. Includes unlimited reading time and Standard Read Aloud voice.
- Complete: Perfect for advanced learners and researchers needing full, unrestricted access. Unlock 1.5M+ books across hundreds of subjects, including academic and specialized titles. The Complete Plan also includes advanced features like Premium Read Aloud and Research Assistant.
We are an online textbook subscription service, where you can get access to an entire online library for less than the price of a single book per month. With over 1.5 million books across 990+ topics, we’ve got you covered! Learn about our mission
Look out for the read-aloud symbol on your next book to see if you can listen to it. The read-aloud tool reads text aloud for you, highlighting the text as it is being read. You can pause it, speed it up and slow it down. Learn more about Read Aloud
Yes! You can use the Perlego app on both iOS and Android devices to read anytime, anywhere — even offline. Perfect for commutes or when you’re on the go.
Please note we cannot support devices running on iOS 13 and Android 7 or earlier. Learn more about using the app
Please note we cannot support devices running on iOS 13 and Android 7 or earlier. Learn more about using the app
Yes, you can access Medical Genetics in the Clinical Practice of ORL by R. L. Alford,V. R. Sutton, Patrick J. Bradley in PDF and/or ePUB format, as well as other popular books in Medicine & Communication Studies. We have over 1.5 million books available in our catalogue for you to explore.